

Ausmed is a Trusted Information Partner of Healthdirect Australia. Verify here.


© 2026 Ausmed Pty Ltd (ABN: 33 107 354 441)
A completion certificate is not evidence that someone can do a good job. Assess support workers against what the work requires, in the setting where they do it, and hold the evidence against their record for as long as you need it.
Book a walkthroughA support worker can finish a module on enteral feeding and still not be safe to run a PEG feed in a participant's home. What most large providers don't have is a way to close the gap that scales past a service manager's memory.
The usual answer is a paper checklist in a site folder, which holds up until you need to know who is currently assessed for high intensity supports across 40 sites and 1,500 workers, or until the Commission asks you to produce the evidence for a worker who left eight months ago.
A single completion tick is not enough to prove competence.
| Component | What it means | What evidences it |
|---|---|---|
| Knowledge | They understand the process. | Completed by the worker, through assigned learning |
| Skill | They can carry it out. | Observed by a manager, or submitted by the worker |
| Intention | They apply it the way this person needs. | Acknowledged by the worker at the start of the shift |
| Confidence | They can do it alone, on shift. | Self-rated by the worker at the end of learning |
| Practice | They have done it recently enough to still count. | Confirmed by the worker after the shift |
A register records what was arranged. Readiness is about what a worker can do in front of a participant this week, and most of what a large provider holds today cannot tell the two apart.

The module is finished, so the box is ticked. Nobody watched the worker perform the skill, and the record cannot tell you whether anybody ever did.

Signed checklists exist, on paper, in forty buildings. Producing them centrally means forty phone calls, and producing them for a worker who left means a search.

Assessment bottlenecks on the clinician or senior practitioner everyone trusts. When they are on leave, competency work stops, and when they leave, it restarts.

A worker was assessed as competent, in 2023. Nothing in the system distinguishes that from assessed last month, so the register reads as green either way.

Competence demonstrated in a training room says little about competence at 6am in a participant's bathroom with the equipment that is actually there.

The Commission can ask about a worker who left eight months ago. If their assessment record was local to a site or a supervisor, the answer is a reconstruction.
General Manager Education and Clinical Specialties, disability and aged care provider
Each of the below may have a different assessor, a different setting and a different standard of evidence. But, they are built and run from the same competency library in Ausmed.
See it with your own supportsPEG feeding, tracheostomy, ventilator and catheter support assessed against the specific protocol, criterion by criterion, by a named assessor.
Prompting, assisting and administering are three different competencies with three different thresholds. Assess them separately.
Transfers assessed against the participant's own equipment, in their own home.
Verify that a worker can implement this participant's plan, not that they understand behaviour support in general.
Confirm the worker is authorised, trained and currently assessed before they can be allocated to the shift.
Track a new starter through their first 90 days against staged milestones.
Build observable criteria against your own procedures and participant protocols, set the evidence required, and choose who is permitted to sign it off. Start from a template where one fits.
Ausmed Competency™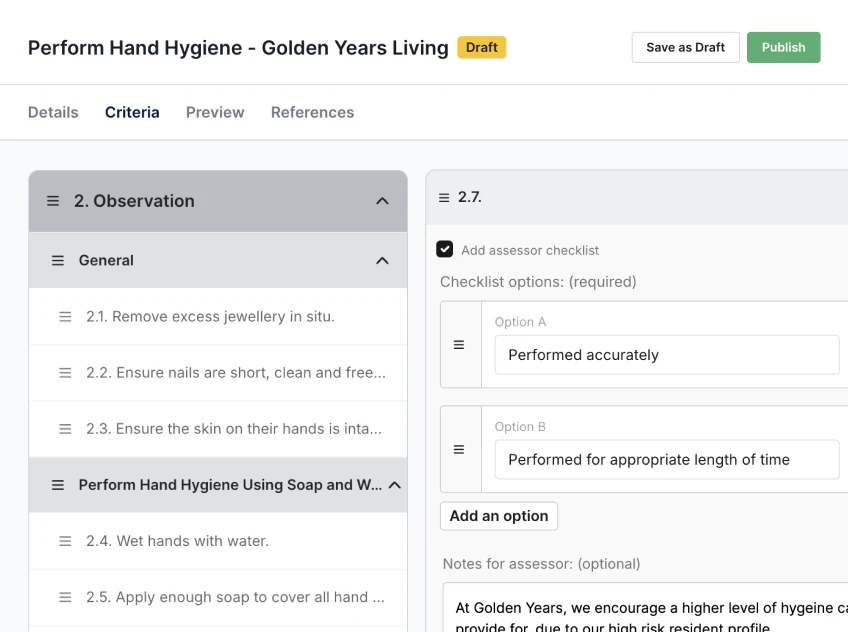
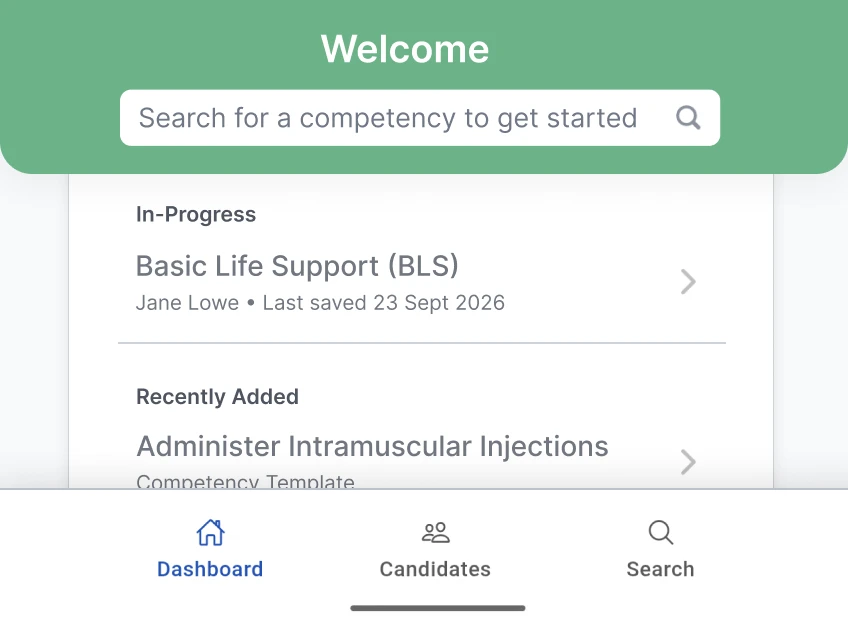
Team leaders complete the assessment on a phone, in the setting, at the time. The record is timestamped and attributed, so there is no gap between the observation and the evidence.
Competency status is exposed to your rostering system, so a worker who has not been signed off can't be allocated to a support that requires it, and a coordinator sees why before they try.
Skill-based rostering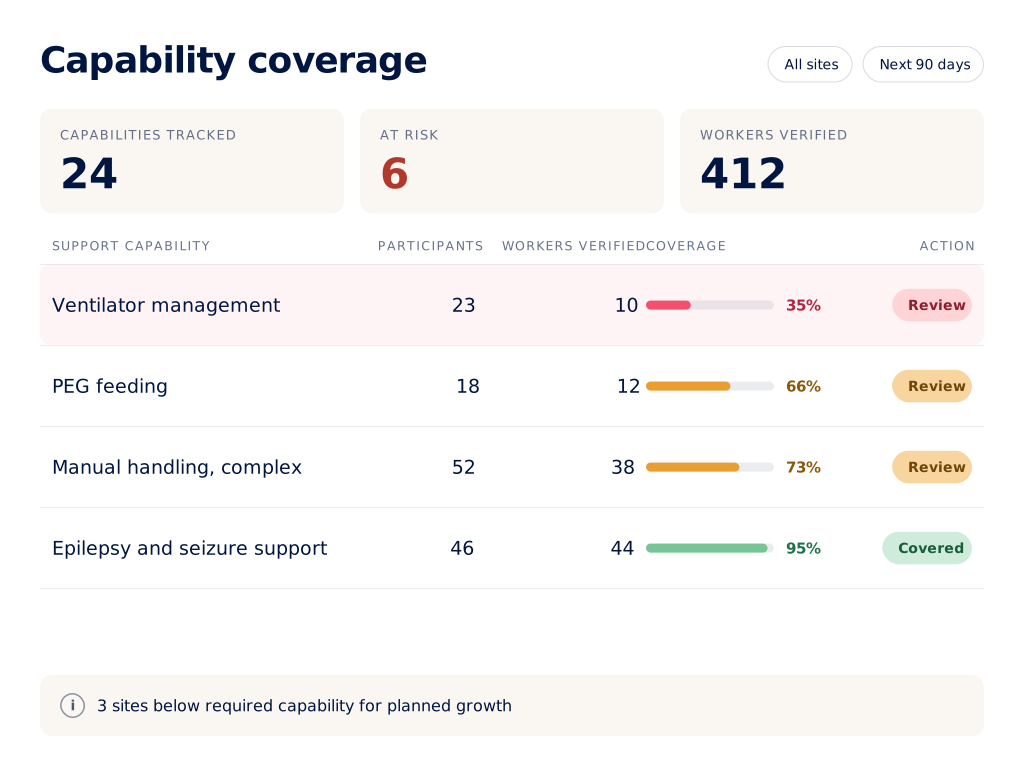
Competency templates, digital assessment authoring and assessor sign-off across every site.
Ausmed Competency™The training that precedes an assessment, and the remediation that follows a gap.
Ausmed Learn™Assessed, not yet competent and overdue, reported by site, team and support type.
Ausmed Analytics™ NDIS Practice Standards · Core Module
"Each participant's support needs are met by workers who are competent in relation to their role, hold relevant qualifications, and who have relevant expertise and experience to provide person-centred support."
Competent is a claim about what a worker can do in front of a participant. A second indicator asks you to evaluate the effectiveness of the training you deliver. Completion data answers neither.
In relation to their role is why one organisation-wide register does not satisfy the standard. Competent in a SIL house with two residents on enteral feeding is not competent in community access.
Read the Core ModuleAssessments map to the High Intensity Support Skills Descriptors, which describe the practice expected for each high intensity support. Where a descriptor expects more than a module, the assessment is signed off by a named assessor in the setting where the support is delivered.
Audit preparednessBring one support type you're not confident about, and we'll show you what assessing it would look like.
You decide, per assessment. Some providers restrict high intensity sign-off to a clinical lead or registered nurse, and allow team leaders to assess manual handling. Assessor permissions are set on the competency, not on the person's job title alone.
A competency can be scoped to one participant's protocol, so a worker assessed on that person's enteral feeding regime is not automatically cleared for someone else's.
Their manager, or a nominated user, is notified automatically. The remediation you take is documented in an Action Log against that outcome, so there is a structured record of how it was resolved rather than a conversation nobody wrote down.
Ausmed is a Trusted Information Partner of Healthdirect Australia. Verify here.